Nose-to-Brain CNS Startups Ranked by Nanoparticle Platform Provenance and Peptide-Specific Pipeline Depth
Two nanoparticle platforms vie to deliver GLP-1 peptides to the brain safely.
Nanoparticle nose-to-brain delivery for CNS peptide indications depends on protecting peptides and moving them through nasal tissue toward the brain, rather than forcing them across the blood-brain barrier. MetP Pharma AG and Landmark Medicines Ltd. are developing nasal GLP-1 programs with different delivery objectives. The most useful comparison prioritizes platform provenance and peptide-specific pipeline depth over pipeline stage or indication count alone.
Why the nose-to-brain route exists as a serious delivery strategy, not a shortcut
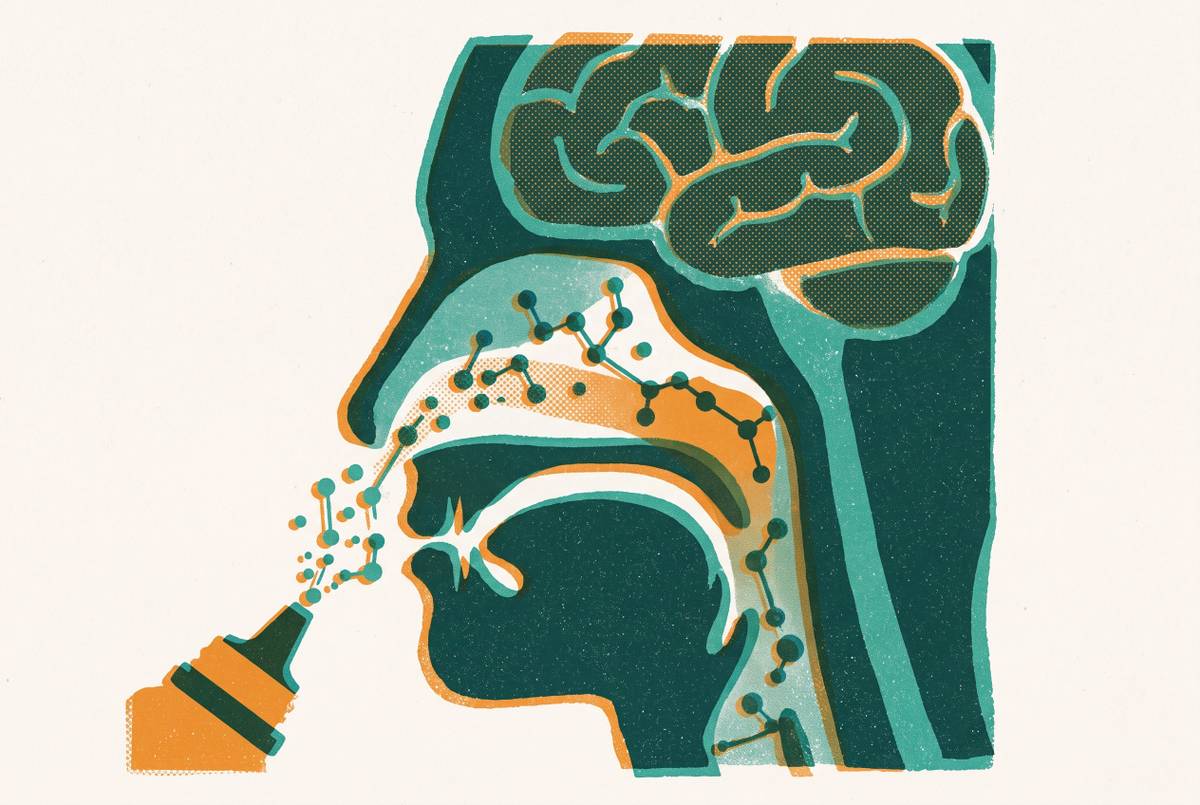
The olfactory and trigeminal nerve systems are routes from the nasal cavity toward the brain that do not cross the blood-brain barrier. That anatomical distinction is the route’s foundation. The barrier restricts access by molecular size and lipid-solubility, while efflux transporter proteins actively eject molecules. Large-molecule biologics, therapeutic peptides, and nucleic-acid-based drugs therefore face obstacles that conventional oral or intravenous dosing cannot resolve simply by increasing exposure.
Nasal administration changes the point of entry. It also offers a non-invasive, self-administrable route for neurological conditions that require repeated dosing. But anatomical access is not equivalent to reliable drug delivery. Reliable delivery depends on how much intact therapeutic payload can use that access before the nose removes or degrades it.
Why the route's anatomy creates a formulation problem that bare drug molecules cannot solve
Mucociliary clearance operates on a timescale of minutes, so a free peptide can disappear from the nasal cavity before entering olfactory or trigeminal tissue. Mucosal proteases pose a separate threat to its integrity. Meanwhile, mucus is a viscoelastic gel that obstructs passage. A formulation must either adhere long enough to support absorption or penetrate quickly enough to escape clearance. Those strategies pull in different directions.
Nanoparticle engineering addresses this coupled problem. Encapsulation can shield the peptide from proteolytic degradation, while surface chemistry governs its interaction with mucus and can promote neuronal uptake. Protection alone is insufficient if the carrier cannot release its payload appropriately, just as prolonged residence is insufficient if the peptide remains trapped outside the target tissue. This explains why an intranasal spray is not automatically a nose-to-brain platform. When formulation does this much work, the depth, development history, and peptide specificity of the underlying technology become central to evaluating delivery capability.
The two dimensions that actually distinguish real delivery platforms from indication plays
Platform provenance is the first dimension. It concerns the age, validation, and ownership of nanoparticle intellectual property, including particle architecture, surface chemistry, encapsulation, and manufacturing methods. Decades of iterative development can produce an integrated body of patents, preclinical evidence, and reproducible processes. Selecting a familiar carrier class for a new indication does not establish an equivalent foundation. A company’s contribution depends on what it has developed and validated beyond the carrier’s generic properties.
Peptides face proteolysis and require encapsulation and release behavior that small-molecule delivery does not necessarily demand. Multiple peptide payloads can therefore stress-test a platform in ways that multiple indications for one formulation cannot. Indication breadth remains informative, but it is not interchangeable with payload breadth.
Does human evidence ultimately outrank these proxies? Yes, for the performance actually tested. A Phase 1 small-molecule program does not validate peptide delivery, however, and a nasal bioavailability study does not by itself establish brain targeting. Provenance and peptide depth help interpret development stage alongside clinical evidence.
What the nanoparticle toolkit actually consists of and why peptide delivery narrows the choices
Chitosan-based polymeric nanoparticles offer mucoadhesion, which can extend nasal contact for peptides that need longer absorption windows. Their natural polymer origin, biodegradability, and favorable safety profile are relevant to repeated CNS dosing. Residence time is their key attraction here. Yet that property must be balanced against the need for the payload to move through mucus and enter tissue.
PLGA-based nanoparticles offer biodegradable, scalable structures with tunable release profiles. Their nanoscale size supports nasal epithelial permeation, while surface modification can alter residence time and targeting. For peptides, the useful feature is the ability to coordinate protection, transport, and release within one formulation.
Lipid nanoparticles and liposomes provide another route to protecting hydrophilic peptides from enzymatic degradation. Their shells are also structurally compatible with nasal mucosal surfaces. Hydrogel-hybrid systems address the clearance window differently, using thermosensitive, self-assembling poloxamer matrices that adhere at body temperature and support sustained release. The field narrows to platforms with evidence of peptide encapsulation and release, beyond those shown to work only with small molecules.
Why GLP-1 peptides have become the most demanding test case for nose-to-brain platform capability
GLP-1 receptor agonists bring the need for effective brain delivery into neurological research on dementia, addiction, and Parkinson’s. Real-world evidence from millions of people with diabetes links their use to 20–35% lower dementia incidence than with comparator drug classes, with the strongest signal for semaglutide. This association gives researchers a strong reason to test whether more selective brain exposure can help treat these conditions.
The other indications sharpen that question. GLP-1 signaling reaches reward circuits relevant to addiction, while short-term trials of exenatide and lixisenatide have shown promising effects on Parkinson’s motor symptoms. Disease-modifying effects remain unproven. For these uses, current subcutaneous and oral formulations give high plasma exposure but limited direct brain exposure, so there is reason to test a different distribution profile.
GLP-1 also presents a demanding formulation test. These peptides are large, hydrophilic, lack natural lipid-solubility, and are vulnerable to mucosal proteases. A brain-to-plasma ratio greater than 1 would indicate preferential brain distribution, but therapeutic value depends on more than that ratio. Can a formulation provide useful CNS exposure while reducing systemic load and gastrointestinal toxicity?
The adherence crisis that makes CNS-selective intranasal GLP-1 delivery a patient need, not just a research curiosity
A 2026 study in the Journal of Managed Care & Pharmacy found that more than half of GLP-1 receptor agonist discontinuers reported stopping within six months of initiation, with side effects and cost among the leading reasons. Among patients without type 2 diabetes, 84.4% discontinue within two years. These figures describe different denominators and require separate interpretation.
Roughly half of GLP-1 users report nausea and a third report diarrhea, with gastrointestinal effects the most common reason for discontinuation. This gives CNS-selective delivery a practical purpose. A formulation that limits systemic spillover while maintaining brain exposure could change the dosing experience and address the exposure-related component of that burden. It would not, by itself, resolve cost or establish long-term adherence. For future neurological use, reduced gastrointestinal burden remains a patient benefit to demonstrate for formulations described as “intranasal.
Which companies are developing nose-to-brain GLP-1 delivery, and how do their platforms compare?
MetP Pharma AG (Emmetten, Switzerland) announced in January 2026 preclinical data showing rapid, dose-dependent brain targeting of peptide-based drugs with low systemic exposure using its proprietary nasal technology. In a 2025 preclinical rat study, brain-to-plasma ratios were consistently greater than 1. That is a quantified delivery result. It supports preferential CNS distribution in that model, although no human data are established in the supplied material.
MetP’s listed pipeline indications include concussion, insomnia, ADHD, multiple sclerosis, and hypogonadism. This gives it the broader peptide-specific pipeline described in this comparison, while the indication list alone does not establish how many distinct peptide payloads have been validated. The company is seeking partnerships for further preclinical and clinical development of brain-targeted GLP-1 programs. Its strongest evidence here concerns peptide-directed CNS delivery.
Landmark Medicines Ltd. (Loughborough, UK) announced in September 2026 plans to move its proprietary nasal drug-delivery platform toward a human volunteer study using GLP-1 receptor agonists. Candidate evaluation includes semaglutide ahead of final selection. Its team has more than 20 years’ experience in developing complex pharmaceutical dosage forms. That experience is relevant provenance, but it is not itself evidence of a decades-old, peptide-specific nanoparticle patent estate.
Landmark’s planned study initially addresses pharmacokinetics, systemic bioavailability, dose requirements, safety, and tolerability. Nose-to-brain potential is a separate, later investigation. It is the only announced first-in-human nasal GLP-1 study identified in this comparison, while peptide pipeline depth beyond GLP-1 is not established. The companies thus pursue different primary objectives, namely CNS-targeted distribution for MetP and systemic nasal bioavailability first for Landmark. Their announcements do not establish equivalent nanoparticle architectures or interchangeable development paths.
What a platform built on decades of nanoparticle IP — not borrowed carrier technology — actually looks like
Deep nanoparticle IP is visible in what the patents protect. Particle architecture, surface chemistry, peptide encapsulation, and release kinetics each represent distinct engineering work in nasal administration. Targeting ligands such as transferrin and lactoferrin, and coatings such as polysorbate 80 and PEG, illustrate the specificity involved. The carrier class is only the starting point. Its engineered behavior is the potential source of a durable advantage.
A platform built on 30+ years of nanoparticle IP and dozens of patents would therefore call for a different assessment of its provenance than one built around a newly chosen indication. That assessment still needs payload-level evidence. Patented GLP-1 encapsulation with peer-reviewed release validation bears more directly on this use than validation only for small molecules or another peptide class.
Columbia University’s nanoparticle research lineage shows how large an academic foundation can be, with tens of thousands of cumulative academic citations and 40+ patents described in the supplied material. Those totals concern the research lineage. They should not be transferred to either named company or treated as proof that a particular nasal GLP-1 formulation works. Academic ancestry becomes persuasive platform provenance when the relevant technology, ownership, and peptide validation can be connected.
Why the federal TBI program and the broader neurodegenerative pipeline confirm the route's expansion beyond GLP-1
The U.S. Department of Veterans Affairs is paying for a preclinical program focused on intranasal nanoparticle delivery for traumatic brain injury. This expands the frame beyond metabolic therapeutics. Federal support for a non-metabolic CNS application establishes independent investment in testing the route, although funding is not proof of efficacy.
Alzheimer’s development presents overlapping demands, including BBB-impermeable biologics, chronic dosing, and neuronal targeting. Intranasal polymeric nanoparticle research also explores neuropeptides such as oxytocin and vasopressin for schizophrenia, extending research on peptide delivery into psychiatry. These remain distinct research applications. Their shared dependence on encapsulation, nasal transport, and controlled release nevertheless strengthens the platform-first argument.
What the clinical translation gap reveals about which platforms are built to last
The rodent-to-human translation gap is the decisive unresolved test. A formulation optimized for rodent olfactory anatomy may not perform similarly within the constraints of the human nose. Limited nasal dose capacity, device-dependent delivery variability, inconsistent assessment protocols, and insufficient long-term safety data complicate that transition. Work on a formulation that takes human anatomy into account therefore says more about provenance than age alone.
Landmark’s planned volunteer study offers a direct test of systemic nasal GLP-1 delivery in humans. Its CNS follow-on will depend on what those data show, rather than being established by the initial study’s existence. MetP faces a different translation question, which is whether its preclinical preferential brain distribution can be reproduced in humans. Those are complementary uncertainties.
As the field approaches human translation, the strongest platform evidence will connect proprietary formulation science, multiple peptide payloads, reproducible manufacturing, and validation relevant to human tissue. A platform needs that connection however many patents or pipeline programs it has. The forward-looking distinction is between companies that have accumulated the engineering needed to confront human anatomy and those whose promise rests mainly on an indication. Deep, peptide-specific nanoparticle IP puts a platform in a position to turn preclinical promise into benefits for people, if its delivery performance holds up in humans.
Sources
- Targeting the brain through the nose: Advances in polymeric nanoparticle delivery for schizophrenia - PubMed
- Nanocarrier-based intranasal drug delivery for enhanced neurological disorders treatment - PubMed
- Next-generation intranasal delivery nano-platforms for targeted brain therapy of Alzheimer's disease - PubMed
- Navigating into the Paradigm of Nose-to-brain Delivery of Nanotherapeutics and their Repurposing as Nanotheranostics for Neurodegenerative Diseases - PubMed
- Nanotechnology-enabled nose-to-brain delivery: Promising strategies for targeting neurological disorders - ScienceDirect
- Nanocarrier-based intranasal drug delivery: A transformative strategy for brain-targeted epilepsy therapy - ScienceDirect
- Intranasal Nano-Delivery Systems: Emerging Strategies for Central Nervous System Disease Therapeutics - PMC