Pipeline Architecture of Early-Stage Intranasal CNS Peptide Companies Built Around Proprietary Nanoparticle Platforms
Shared nanoparticle design decides which brain targets and peptides a pipeline can reach.
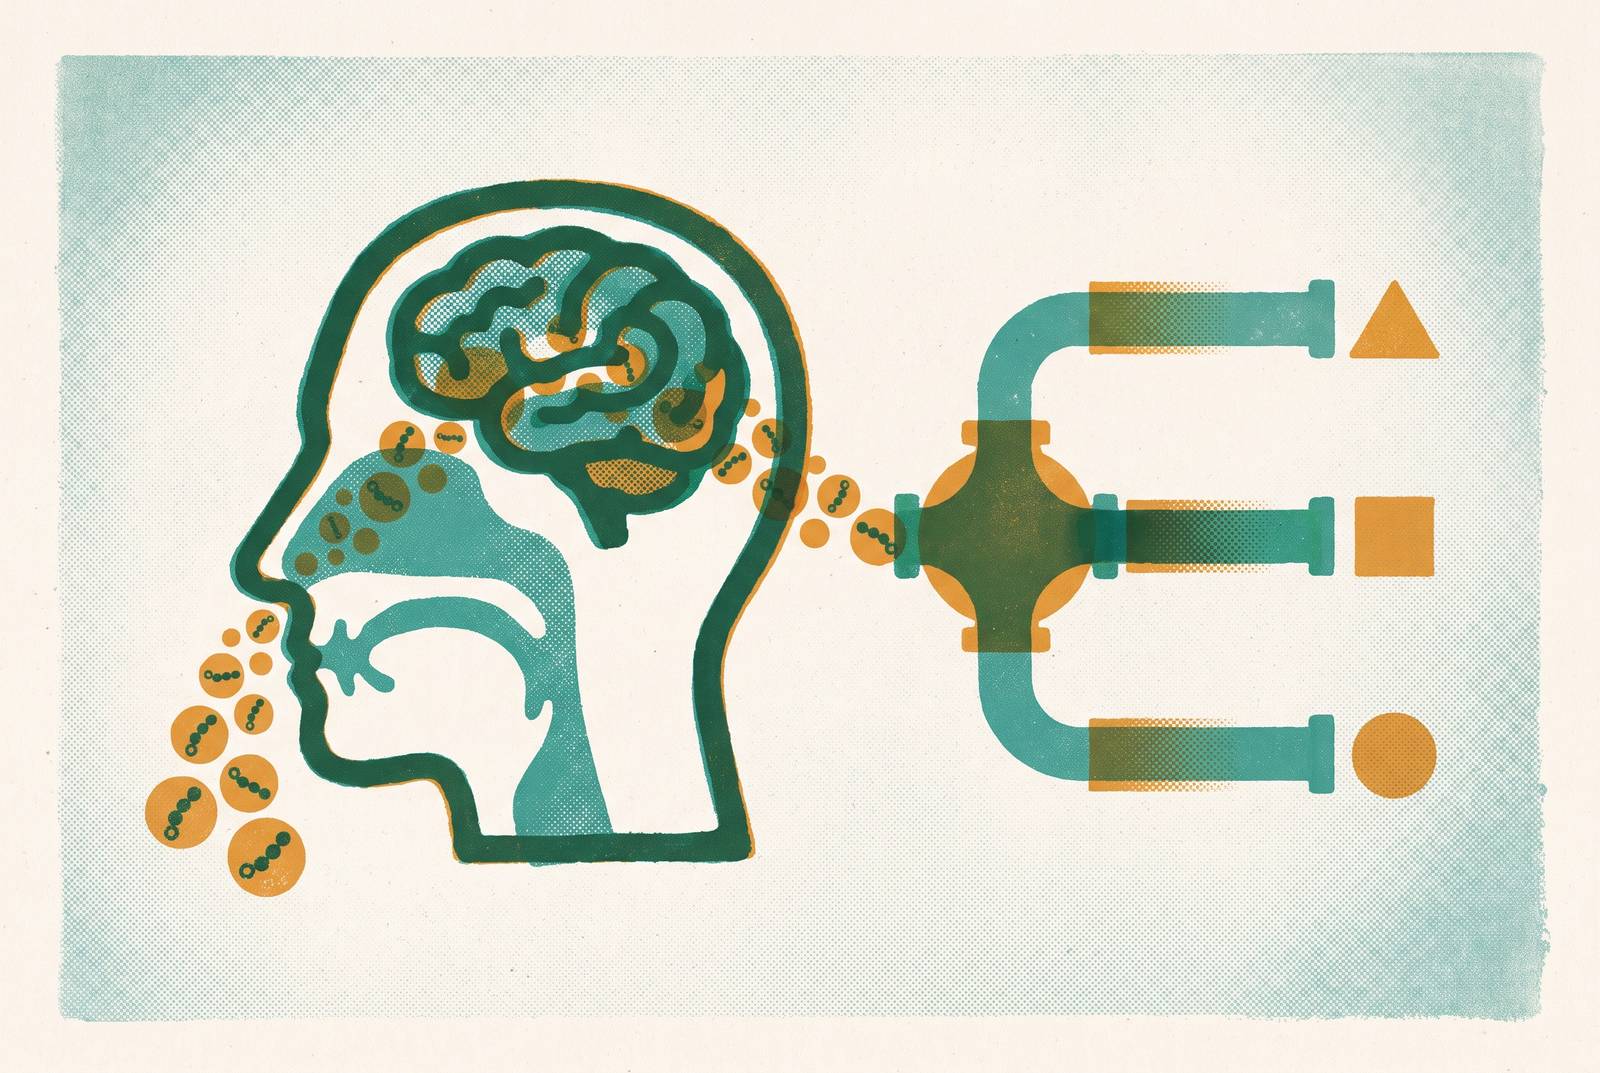
Nanoparticle nose-to-brain delivery for CNS peptide indications aims to protect peptides in the nose and direct them toward neural pathways that bypass the blood-brain barrier. For early-stage companies, the proprietary platform determines more than delivery efficiency. Its architecture defines which brain targets a pipeline can reach, which peptides can share development work, and how durable its competitive position could become.
Why the nanoparticle platform is the structural logic of an intranasal CNS peptide pipeline, not just a formulation choice
A formulation tool improves the delivery of a chosen drug. A platform architecture helps determine which drugs can be chosen in the first place. That distinction changes how an early-stage pipeline is understood, because particle composition, surface engineering, and manufacturing constrain what can move through the system. The lead molecule is therefore one application of the architecture.
What separates a platform from a single optimized formulation? The answer lies in what remains useful when the payload changes. If particle protection, mucosal uptake, targeting methods, and production processes can serve another compatible peptide, the company has a basis for shared development. If each candidate requires those elements to be rebuilt, a long indication list does not establish a platform.
Why bare peptides fail at the nasal mucosa and what that failure demands of any platform that attempts this route
The nasal mucosa presents three converging obstacles to bare peptides, namely size and hydrophilicity, mucociliary clearance, and enzymatic degradation. Large, water-loving molecules do not pass easily across the mucosa. Mucociliary clearance sweeps material out of the nasal cavity, shortening the opportunity for uptake within an already limited dosing volume. Enzymes leave even less of the peptide intact.
Peptide survival is therefore an engineering requirement. Peripheral GLP-1 illustrates the vulnerability, with dipeptidyl peptidase-4, or DPP-4, degrading it with a half-life of less than two minutes. That peripheral measurement explains why protection cannot be assumed. A route around the blood-brain barrier is of little use if the therapeutic does not survive the approach.
Polymeric nanoparticles can protect their payload, extend nasal residence, and provide size and surface properties compatible with olfactory uptake. Lipid-based carriers offer related advantages in solubility, permeation, and protection against degradation. All these functions must work together in one formulation. Reproducing that combination across compatible peptides establishes the route’s minimum platform capability.
How do peptides reach the brain through the nose, and why does that require platform engineering?
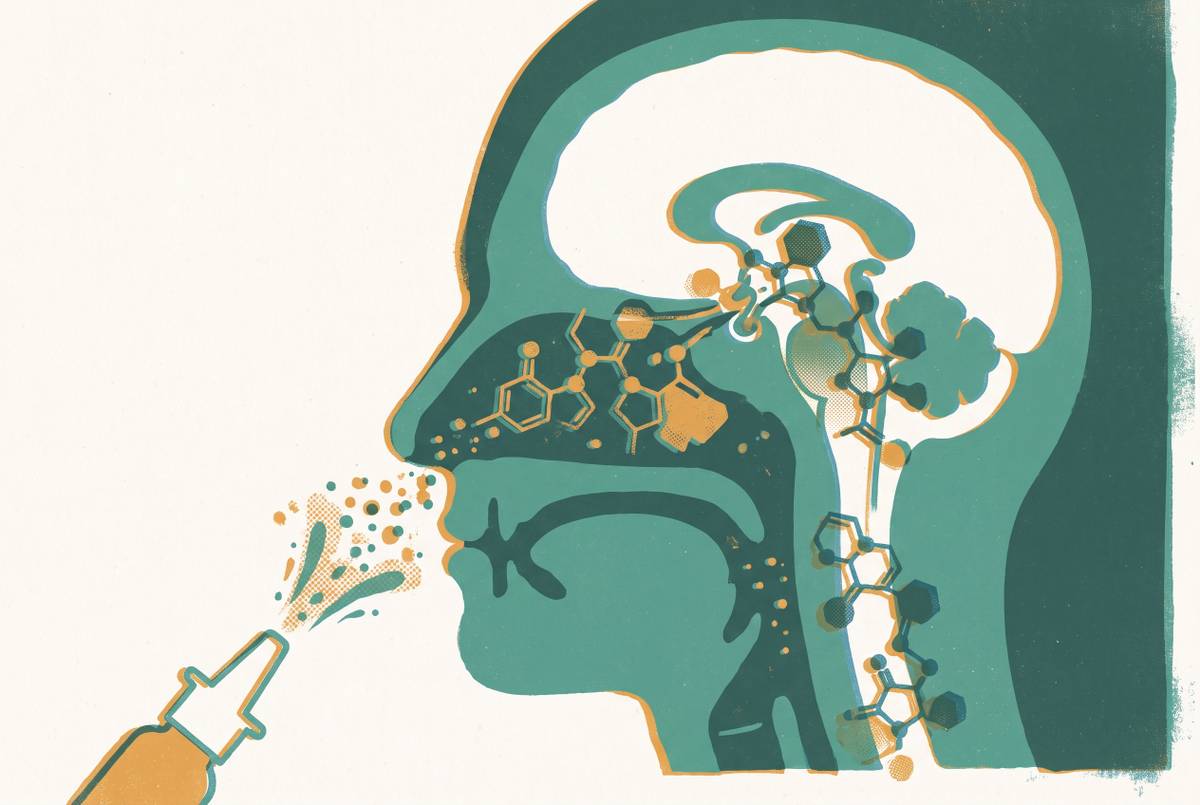
The olfactory and trigeminal pathways provide direct anatomical routes from the nasal cavity to the CNS. Olfactory receptor neurons in the upper nasal cavity project axons through the cribriform plate into the olfactory bulb. Transport can occur intracellularly over hours or extracellularly through perineural spaces over minutes. Trigeminal nerve endings in the respiratory epithelium provide a separate route toward the brainstem.
These routes bypass the blood-brain barrier. Nasal administration can also lead to systemic absorption or lymphatic drainage, but those routes do not supply the same selective brain-targeting rationale. Absorption after nasal dosing therefore does not, on its own, show direct neural delivery. The platform must reach the anatomy that makes the route useful.
A spray must first reach the relevant nasal region, while the particle surface must support transport from that region. Tunable surface chemistry, including targeting ligands, coatings, and cell-penetrating peptides, provides ways to influence the second step.
How nanoparticle material choice and surface architecture translate directly into which CNS regions a platform can reach
Material choice governs protection, release kinetics, and residence time. PLGA, or poly(lactic-co-glycolic acid), is extensively used for polymeric nanoparticles because it supports controlled and sustained release, enhanced stability, and prolonged nasal residence. Solid lipid nanoparticles and nanostructured lipid carriers offer complementary delivery profiles. Dendrimers and nanoemulsions further broaden the design space.
Structural novelty can also change the delivery window. Conejos-Sánchez et al. (2026) describe a star-shaped poly-L-glutamate nanocarrier integrated with a depot-forming hyaluronic acid hydrogel, HA-CP, Yalic®. The system extended nasal residence to approximately four hours and increased the total amount that accumulated in the brain, and it was well-tolerated. The differentiating feature was the combined carrier-and-depot architecture.
Total accumulation, however, does not establish access to every therapeutic target. Which indication the delivery engineering can support still depends on regional distribution, concentration, and how long the peptide stays there. A stable core with swappable targeting ligands offers more room to adjust those properties than an architecture whose targeting strategy cannot be separated from its particle design. That modularity creates options, while each proposed use still requires evidence of relevant CNS exposure.
Why GLP-1 receptor biology in the brain makes intranasal CNS delivery a pharmacology thesis, not just a convenience argument
GLP-1 receptors are expressed in the hippocampus, frontal cortex, and substantia nigra, regions implicated in cognition, emotion, and motor control. Endogenous GLP-1 is also produced in the nucleus tractus solitarius and intermediate reticular nucleus of the brainstem. It functions as a neurotransmitter in multiple brain regions involved in reward processing. The brain already uses this signaling system.
Where an administered peptide acts matters therapeutically. Systemic GLP-1 therapy relies on analogs engineered for stability, but systemic exposure does not necessarily provide the desired exposure at neurological targets. An intranasal platform designed to preferentially load the CNS offers a way to test a different distribution of receptor activity. Its purpose is not simply to remove the needle.
Possible roles in dementia, Parkinson’s disease, and addiction make that experiment scientifically relevant. GLP-1 signaling in the mesolimbic reward system provides a rationale for studying addiction biology, just as receptor expression in other regions supports neurological investigation. The presence of receptors and promising neurological signals do not show that a treatment works. The hypothesis is that better central targeting could improve neurological outcomes while reducing peripheral side effects.
How the multi-peptide architecture of an intranasal nanoparticle platform creates a pipeline rather than a single-molecule program
That delivery hypothesis need not belong to GLP-1 alone. Peptides with compatible physicochemical profiles can share particle materials, surface engineering, mucosal penetration strategies, and manufacturing processes. Changing the payload can then involve incremental reformulation. Compatibility is the condition that makes reuse credible.
Intranasal programs have explored insulin for metabolic brain signaling, oxytocin for social and stress circuits, orexin-A for arousal and appetite, and GHRH for the growth hormone axis. These examples illustrate the range of CNS-active peptide payloads under consideration. They do not establish that one formulation can accommodate all of them. A platform earns that breadth through demonstrated transfer of its delivery capabilities.
Anatomical access also shapes expansion within a peptide class. A system that reaches reward circuits gives researchers a reason to study addiction, while access to the hippocampus supports studies of cognition and dementia. Access to the substantia nigra could support work on Parkinson’s motor symptoms. Once validated, shared delivery engineering makes such programs extensions of an existing system, although each retains its own pharmacological and clinical uncertainties.
The adherence failure of injectable GLP-1s as the market condition that makes the intranasal platform architecturally timely
Discontinuation of injectable GLP-1 therapy has several documented causes, including adverse drug reactions, cost concerns, and non-adherence. Gastrointestinal adverse events such as nausea and vomiting require careful dose titration to reach efficacious exposure. The burden of needles is a separate problem for patients. Treating abandonment solely as a failure of patient compliance overlooks these design constraints.
A nasal route removes the need for injections, but whether it is easier to tolerate depends on its effects. If preferential CNS delivery reduces peripheral receptor activation, it could reduce the peripheral contribution to gastrointestinal side effects. Changing the route alone does not show that it achieves that exposure profile or address concerns about cost. The commercial opening therefore rests on a pharmacological result that the platform must demonstrate.
The rodent-to-human translation gap as the defining technical risk every platform in this space must answer
Human nasal anatomy is the strongest objection to extrapolating promising rodent results. The olfactory epithelium occupies approximately 50% of nasal surface area in rodents but only a small fraction in humans. A formulation that readily encounters its target in a rodent may not do so in a person. Preclinical brain concentrations cannot be assumed to survive that anatomical change.
Limited nasal dose capacity constrains administration, and device-dependent variability complicates reproducible deposition. Without standardized assessment protocols, it is harder to make sense of results across programs. Insufficient long-term safety data also leaves chronic use unresolved.
Manufacturing scalability and regulatory pathways add further uncertainty to translating nasal delivery from rodents to humans. Most programs remain anchored in preclinical concepts, and no nose-to-brain peptide formulation has received FDA approval as of 2026. A strong result in rodents can support more development without showing that a delivery system is ready for use in humans.
How platform design choices — mucoadhesion, ligand engineering, and device integration — directly reduce translation risk rather than ignore it
Mucoadhesive natural polymers, including chitosan, alginate, and gelatin, extend residence by adhering to the mucosal surface. This gives uptake more time before clearance removes the formulation.
Retention alone does not establish effective olfactory targeting. Surface ligands such as transferrin and lactoferrin can improve targeting, while polysorbate 80 and PEG coatings can enhance transport efficiency. Cell-penetrating peptide functionalization provides another means of supporting transport through the olfactory pathway. These are tunable components whose combined performance in humans remains to be demonstrated.
Developing the device and formulation together aims to make upper nasal deposition more consistent and free particle performance from dependence on a generic spray. Tests in physiologically relevant models, including ex vivo human tissue, can then show more directly how well targeting works in humans. A platform combining retention, surface targeting, and deposition control addresses more sources of translation risk than one built around only one of those functions.
Why platform IP depth — not any single preclinical result — determines competitive durability in this emerging class
Those interdependent functions also define what intellectual property can protect. Composition patents, surface modification methods, manufacturing processes, and indication-specific applications each protect a different part of a delivery architecture. A single drug-particle formulation patent has a narrower scope of application. The extent of the IP estate’s coverage of the reusable system matters strategically.
A study backs a scientific claim, while patents and the know-how built up over time affect how easily another developer can copy the approach. Deep protection cannot substitute for effective delivery. A promising experiment alone also does not show that a developer can stay ahead of competitors.
A company that achieves reproducible nanoparticle scale-up for one peptide may have a process advantage when developing a compatible second candidate. Regulatory experience can accumulate in the same way as programs confront nanoscale formulation and device questions. The resulting advantage comes from reusable capabilities, while new payloads and indications still introduce risks that shared infrastructure cannot eliminate.
What the platform architecture framework means for evaluating early-stage intranasal CNS peptide programs
For clinicians, scientific peers, investors, and informed observers, the practical implication is to evaluate the platform before treating the lead molecule as a proxy for the company. Does the design explicitly address human olfactory targeting through retention, ligand engineering, and deposition control, or does its case depend on rodent extrapolation? The distinction is visible in the development plan. Human-relevant validation gives those engineering claims a more demanding test.
Does the IP cover composition, surface engineering methods, and manufacturing processes, or only a particular drug-particle combination? That question separates protection of one product configuration from protection of capabilities that could support several programs. It also connects scientific design to the difficulty of reproducing the platform.
Finally, do the planned indications match the CNS access that has been shown? Each proposed program should have a clear relationship to the delivery architecture, rather than appearing because its disease happens to involve the brain. A coherent pipeline makes that relationship examinable before clinical success is known. As this field advances, the decisive evidence will be whether the architecture can support human delivery and then extend to another compatible peptide without being rebuilt.
Sources
- Targeting the brain through the nose: Advances in polymeric nanoparticle delivery for schizophrenia - PubMed
- Pharmacokinetics and Pharmacodynamics of Intranasal Solid Lipid Nanoparticles and Nanostructured Lipid Carriers for Nose-to-Brain Delivery
- Full article: Intranasal Nano-Delivery Systems: Emerging Strategies for Central Nervous System Disease Therapeutics
- A rationally designed polypeptide-based hybrid platform for targeted intranasal brain drug delivery - PubMed
- Intranasal Nanoemulsions for Direct Nose-to-Brain Delivery of Actives for CNS Disorders